
Snippet #033: What Your Muscle Oxygen Sensor Is Actually Reading
Near-infrared spectroscopy (NIRS) shines near-infrared light through skin into muscle and reads how much hemoglobin and myoglobin is carrying oxygen. The ratio is reported as muscle oxygen saturation (SmO2), a local signal reflecting the real-time balance between oxygen delivery and oxygen consumption beneath the sensor.
When demand outpaces supply, SmO2 drops; when delivery recovers, it rises. The speed of re-oxygenation after a hard effort is associated with local oxidative and microvascular recovery capacity.
A systematic review of 57 exercise studies by Perrey and Ferrari confirms NIRS as a meaningful marker of skeletal muscle oxidative capacity across sport activities (Perrey & Ferrari, Sports Med, 2018).
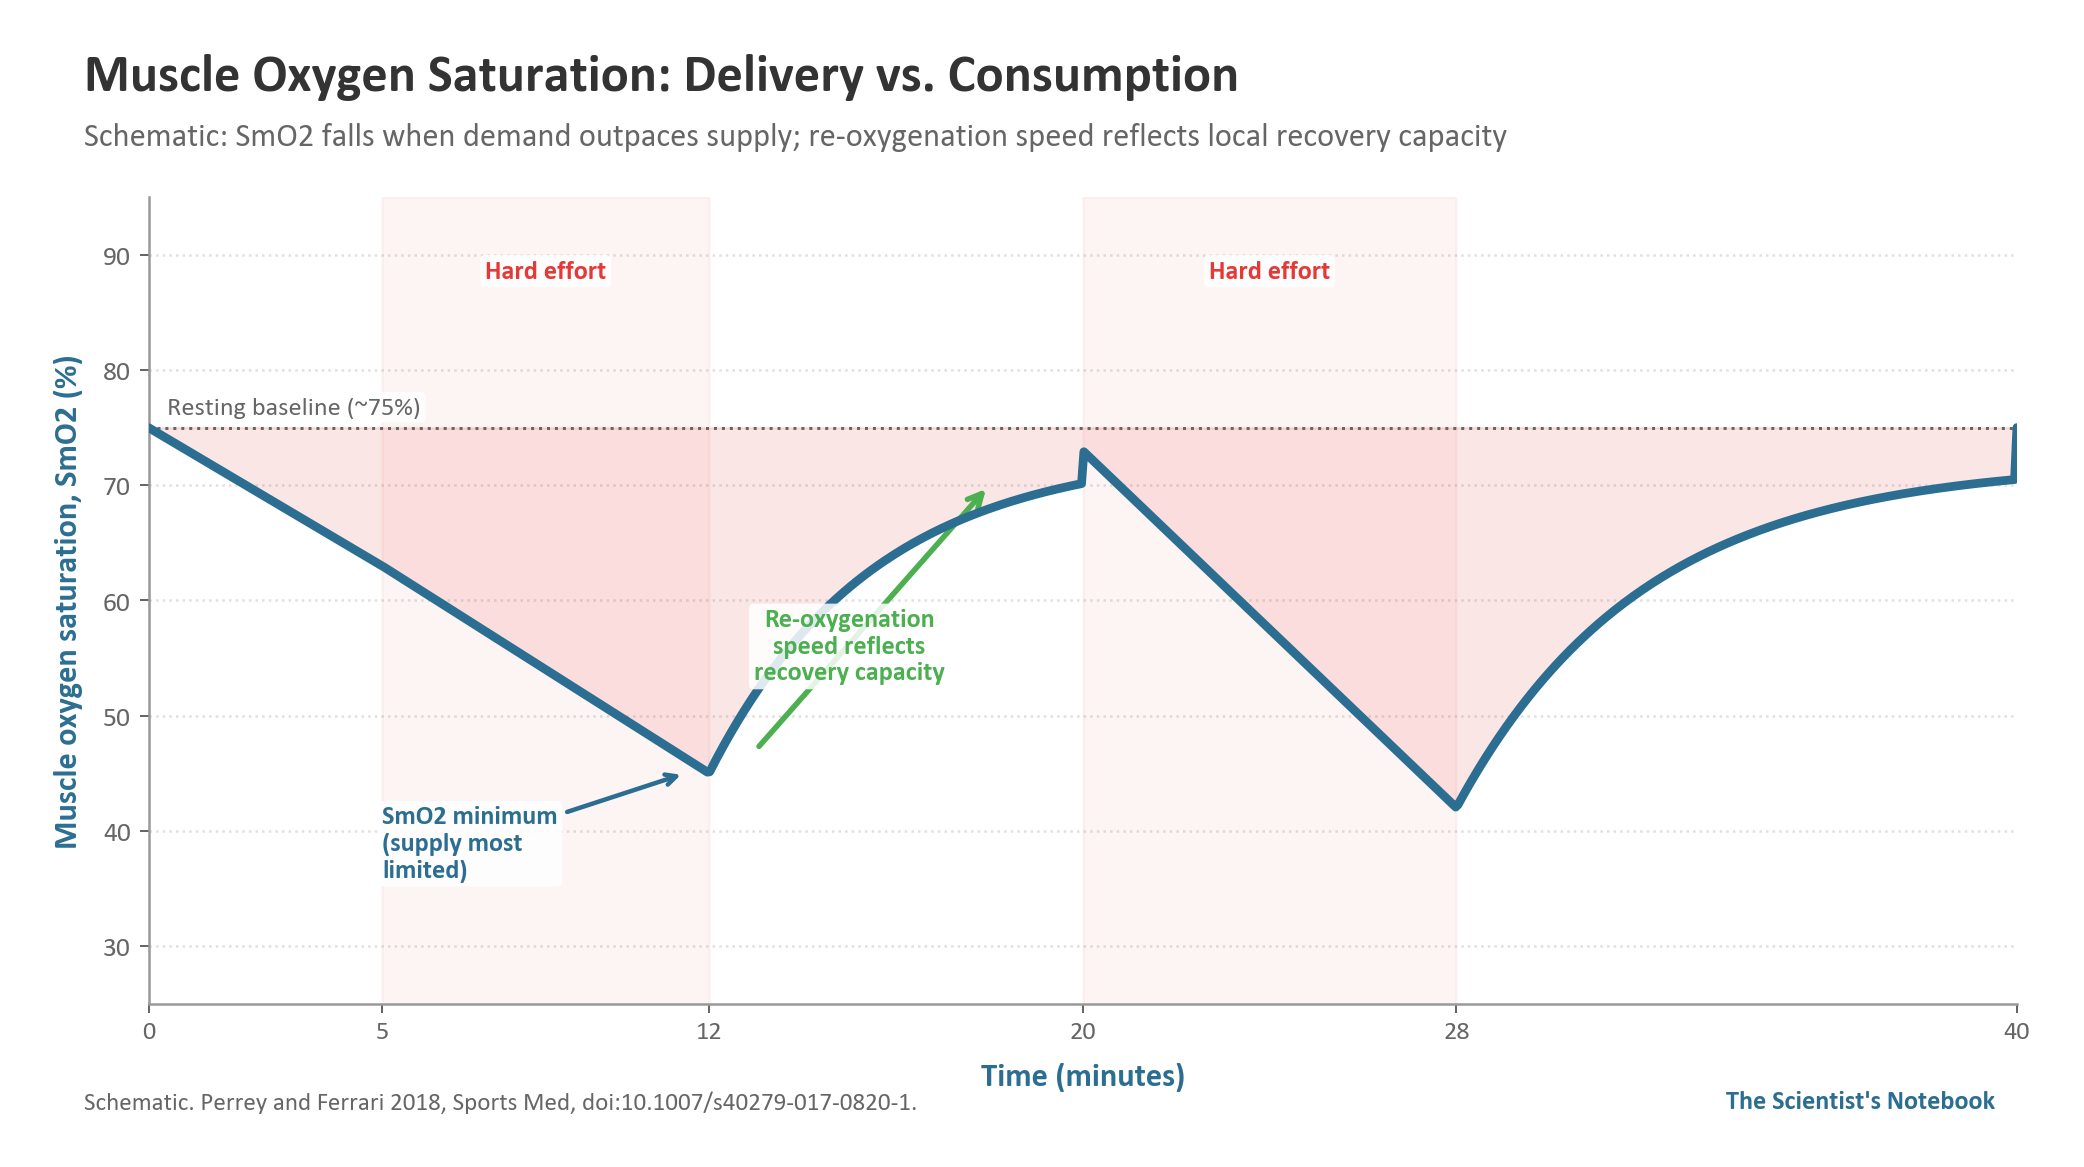
SmO2 captures what whole-body gas exchange cannot: whether the muscle under the sensor is receiving enough oxygen relative to its workload.
Two athletes can show the same VO2 at a given power while one muscle group is severely desaturating. Re-oxygenation rate between intervals is associated with aerobic fitness and capillary density.
SmO2 is a local, not systemic, measure. Adipose tissue thickness attenuates the signal, sensor placement shifts the tissue sampled, and motion artifacts corrupt readings. A vastus lateralis reading says nothing reliable about the calf or cardiovascular system.
---
If you have 60 seconds, I would value your anonymous feedback. You can share it here.
---
### Health disclaimer
This post discusses endurance-training science for educational purposes. It is not medical advice, not a diagnosis, and not a substitute for clinical care. Individual response to training, sleep deprivation, and multi-day exertion varies substantially, and what applies to a research cohort or a world-class athlete may not apply to you. > Consult a qualified physician, sports medicine specialist, or registered dietitian before changing your training, fuelling, or sleep strategy if you have a cardiovascular, metabolic, psychiatric, or sleep-related condition; are recovering from injury or illness; are pregnant; are on medication that affects heart rate, hydration, glucose regulation, or sleep; or have concerns about exercise tolerance. > Ultra-endurance events impose real physiological and psychological loads. Persistent chest pain, fainting, acute confusion beyond the predictable late-race window, severe dehydration, sustained loss of coordination, or any mental-health symptoms that outlast the immediate post-event dip warrant professional care and are not signals to push through. > No outcome is guaranteed. The protocols, anchors, and case material in this post are descriptive, drawn from peer-reviewed evidence and a guest contributor's lived experience, and should be treated as inputs to an informed conversation with your own coach and clinicians, not as prescriptions.